Türkçe
 Français
 Deutsch
 Italiano
 Español

Rheumatic heart disease is permanent damage caused to the heart valves by the immune system after throat infections experienced during childhood. This condition, which develops especially after beta-hemolytic streptococcus infection, disrupts the working order of the heart by causing narrowing or insufficiency in the valves. This disease, which is a preventable health problem when detected early, can be treated in modern medicine with advanced interventional techniques without the need for open surgery. Because the symptoms progress insidiously, regular checkups and proper management strategies are vital for protecting heart health. Innovative solutions applied today rapidly improve patients’ quality of life and offer a healthy future.
What Is Rheumatic Heart Disease and How Does It Begin in the Body?
The story of how this disease begins is actually based on a rather unfortunate mistake made by our body’s defense system, namely the immune system. Let us approach this more simply. Our body produces special defense cells, that is, antibodies, to fight the group A beta-hemolytic streptococcus bacterium that settles in our throat. These antibodies are programmed exactly like soldiers, and their only purpose is to find and destroy the bacterium. However, the protein structure on the outer surface of the bacterium and the protein structure of the muscle and valve cells in the human heart are incredibly similar.
Because of this condition, called molecular mimicry in medicine, the defense soldiers produced by the body do not stop even after they destroy the bacterium. They begin to attack the heart valves, joints, and sometimes the nervous system, mistaking them for enemies because of their similar structure. In other words, the body begins to harm itself. This friendly fire causes intense inflammation in the heart. Even after this first feverish and painful process, called the acute phase, passes, the inflammatory process initiated in the heart valves continues to progress insidiously. After this silent battle lasting for years, the heart valves lose their flexibility, thicken, and become unable to perform their function.
What Are the Acute Phase Symptoms of Rheumatic Heart Disease?
The period of acute rheumatic fever, when the disease first appears, is the time when a storm practically breaks out in the body. During this period, complaints are seen in many different organs due to the excessive response of the immune system. Severe joint problems are among the most common complaints. Pain and swelling that begin in one knee may decrease after a few days and move to the other knee or ankle; this is called migratory arthritis. In addition, silent or obvious heart complaints may occur due to heart involvement. This condition, which begins in childhood, can sometimes be difficult for families to notice because the symptoms may be confused with a simple flu or growing pains.
The most common acute phase symptoms are as follows:
- High fever
- Joint pain
- Joint swelling
- Skin rashes
- Subcutaneous swellings
- Involuntary muscle movements
- Palpitations
- Shortness of breath
- Fatigue
When several of these symptoms are seen together, physicians take the condition very seriously. Pale-centered, ring-shaped rashes appearing on the skin or painless hard lumps over bony prominences also provide important clues in diagnosing the disease. Neurological pictures that occur especially as a result of nervous system involvement and cause the patient to move their hand, arm, or face involuntarily are considered a direct warning of rheumatic fever.
Which Tests Are Performed to Diagnose Rheumatic Heart Disease?
Detecting the damage caused by rheumatic heart disease on the heart is now quite easy and painless with today’s technology. In the past, diagnosis was attempted only through murmurs heard by listening with a stethoscope, whereas today we can see the inside of the heart in the finest detail. Even if the patient has no complaints, it is possible to detect a small damage beginning in the heart valves at a very early stage.
The main diagnostic tests performed are as follows:
- Echocardiography
- Electrocardiography
- Blood tests
- Throat culture
- Chest X-ray
Among these tests, the most important is undoubtedly echocardiography, that is, heart ultrasound. This device creates a moving video of the heart using sound waves. Thanks to its color Doppler feature, the speed of blood passing through the valves, whether there is leakage in the valves, and the thickness of the valve leaflets are measured with millimetric precision. Electrocardiography (ECG) records the heart’s electrical system on paper; it shows whether inflammation has slowed signal transmission in the heart. Blood tests are also an indispensable tool for confirming the level of inflammation in the body and whether the patient has recently had a beta-hemolytic streptococcal infection.
How Does Rheumatic Heart Disease Damage the Heart Valves?
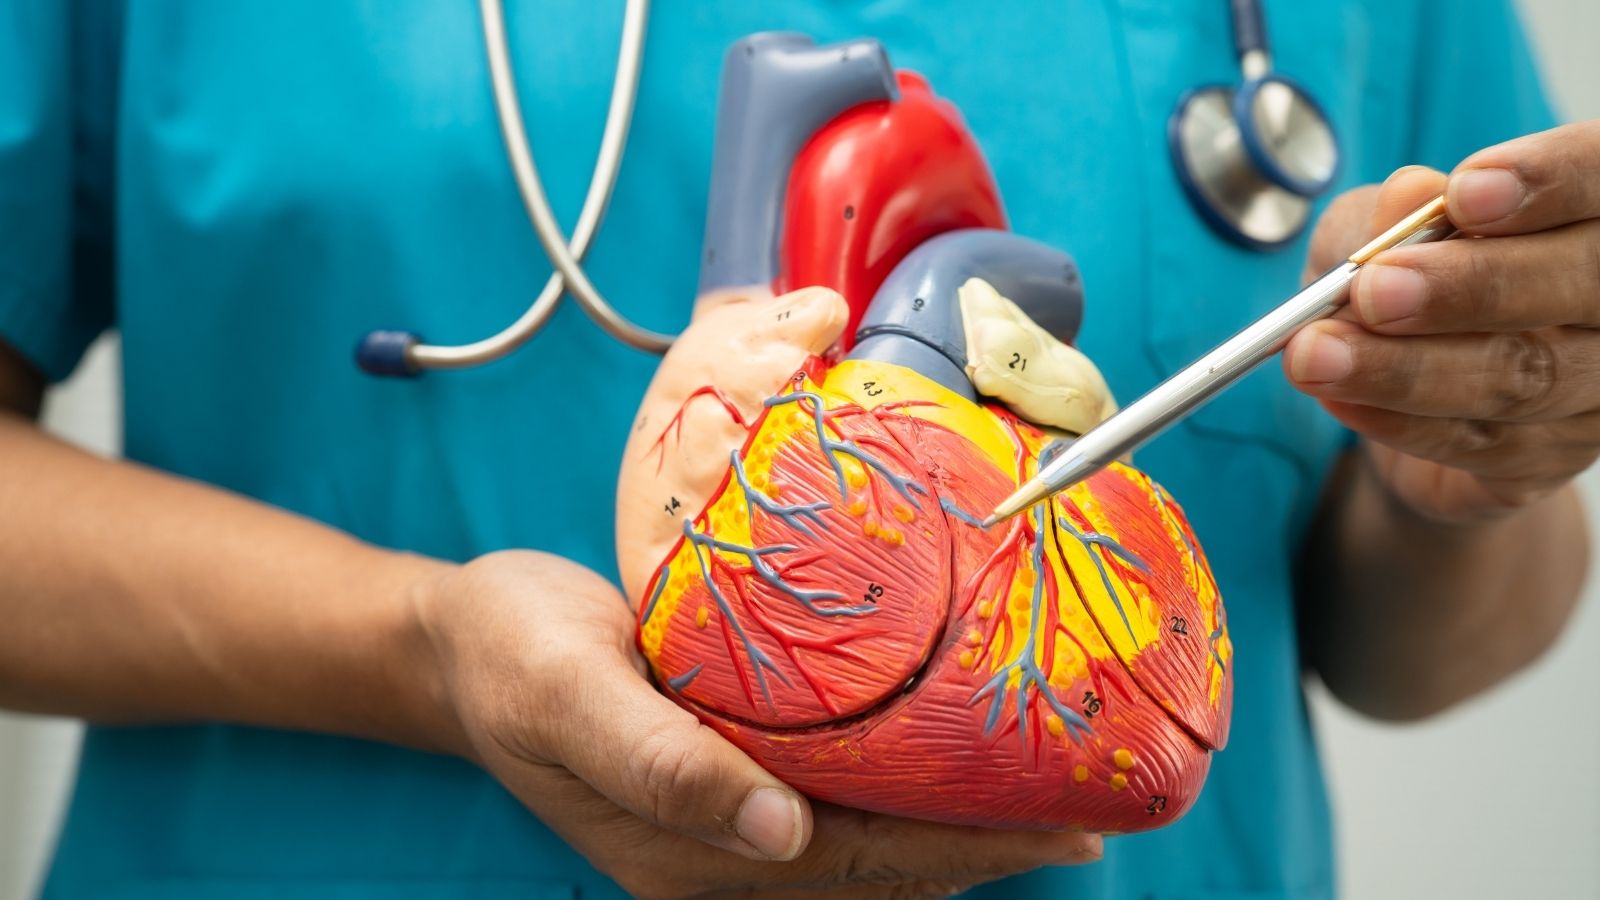
You can think of your heart as a four-room house and the heart valves as the doors between these rooms. The duty of these doors is to ensure that blood flows in the correct direction and never allow it to flow backward. Rheumatic inflammation is like rust that damages the hinges and wood of these doors. In a healthy person, the heart valves are very thin, transparent like onion skin, and extremely flexible. However, as inflammatory attacks assault the valve leaflets, these membranes fill with scar tissue, thicken, and harden.
Over time, this damage progresses further. The junction points that allow the valves to open and close begin to stick together. The opening through which blood can pass gradually becomes smaller; this condition is called “stenosis” in medicine. On the other hand, the thin parachute-cord-like bonds that connect the valves to the heart muscle may also shorten and harden. In this case, the valve cannot close completely and blood leaks backward; this is called “insufficiency.” Sometimes both conditions can be seen together in the same valve.
The most commonly affected heart structures are as follows:
- Mitral valve
- Aortic valve
- Tricuspid valve
When this condition especially affects the left side of the heart, the main system that pumps clean blood to the body becomes impaired. Blood begins to pool backward toward the lungs, and patients constantly feel tired, breathless, and weak.
What Are the Non-Surgical Treatment Options for Rheumatic Heart Disease-Related Stenosis?
In the past, when a narrowing was detected in a heart valve, the only option for patients was difficult open-heart surgery in which the chest was split open, the heart was stopped, and the patient was connected to a machine. However, today, thanks to the field we call interventional cardiology, the inside of the heart can be reached through vascular routes using very thin tubes. These interventional procedures, also known as closed methods, have changed the fate of rheumatic heart diseases.
Especially in the condition called mitral stenosis, where the valve between the left atrium and the left ventricle narrows, non-surgical treatment options are offered to suitable patients. Without making any incision in the chest, the narrowed valve can be widened by entering only through the vein in the groin area. While this approach saves the patient from the psychological and physical burden of surgery, it also accelerates the recovery process to an incredible degree. After staying in the hospital for only a few days, patients can return to their daily lives, work, and loved ones with much more energy.
Who Is Suitable for Balloon Treatment for Rheumatic Heart Disease?
This procedure, popularly known as ballooning the heart valve and medically called Percutaneous Mitral Balloon Valvuloplasty, is an extremely successful method, but unfortunately it cannot be applied to every patient. For the procedure to be performed, the anatomical structure of the valve, meaning its current condition, must be capable of responding to the balloon. If the valve has completely calcified over the years and has hardened almost like stone, the balloon cannot open this valve. Likewise, if there is very serious backward leakage (insufficiency) in the valve along with stenosis, this leakage may increase even more when ballooning is performed.
For this reason, interventional cardiology specialists examine the heart with detailed ultrasound measurements before deciding on the procedure and assign the valve a suitability score.
The main valve characteristics evaluated are as follows:
- Valve mobility
- Valve thickness
- Degree of calcification
- Structure of the subvalvular chords
If the patient’s valve has not completely lost its flexibility, if there is no excessive calcific mass on it, and if the main problem in the valve is caused by the leaflets sticking together, this patient is considered an “ideal candidate” for the balloon procedure. However, if the tests show that the valve is not suitable for ballooning, then it may be decided that the safest approach is surgical valve replacement.
How Is the Balloon Procedure for Rheumatic Heart Disease Performed?
The balloon procedure is performed in sterile rooms called angiography laboratories, where special imaging devices are available. The greatest comfort of this procedure is that the patient does not need to be fully put to sleep, that is, general anesthesia is not required. While the patient is awake and able to communicate with those around them, only the groin area is numbed with local anesthesia. In this way, no pain or discomfort is felt during the procedure.
The process begins by entering the large vein in the groin with a small needle. With the help of very thin wires and tubes called catheters, the right side of the heart is reached. To pass from the right chamber of the heart to the left chamber, a very small hole is opened in the thin membrane between the two atria and the opposite side is crossed. This stage is the part of the procedure that requires the most experience. After reaching the left side, a special wire with a deflated balloon at its tip is placed exactly in the middle of the narrowed mitral valve.
With controlled pressure applied from outside, the balloon is inflated inside the valve. As the balloon inflates, it separates the valve leaflets that have stuck together over the years from their edges and widens the passage area of the valve. After it is instantly confirmed on ultrasound and X-ray screens that the valve has opened sufficiently, the balloon is deflated and removed from the body. At the end of the procedure, the vessel opening in the patient’s groin is closed and the patient is taken to the room to rest.
What Advantages Does the Balloon Procedure for Rheumatic Heart Disease Offer Patients?
The balloon method has many superior aspects compared with surgery, both physically and psychologically. Immediately after the procedure, because the feeling of tightness in the heart disappears, patients feel that their breathing is relieved even when they sit up in bed. This method, which does not create surgical stress, is a major opportunity especially in young patients in terms of preserving the heart’s original tissue.
The main advantages offered by the balloon procedure are as follows:
- No incision scar on the chest
- Short hospital stay
- Rapid return to daily life
- Lower risk of infection
- No need for blood transfusion
- Avoidance of general anesthesia risks
While it takes months for the bones of a patient who has undergone open-heart surgery to heal and fuse, a patient who has undergone the balloon procedure can regain their normal pace within a few days. Since the original valve is preserved, the patient does not need to go through an adaptation process to a mechanical heart valve, and preserving the natural structure is always more beneficial for overall heart health.
Which Methods Are Used When Rheumatic Heart Disease Affects the Aortic Valve?
Although rheumatic disease most commonly affects the mitral valve, the second most frequent target is the aortic valve, the main exit door of the heart. When the aortic valve narrows, the clean blood pumped by the heart cannot adequately reach the body, organs, and brain. In this condition, patients may experience chest pain while walking, their vision may darken, and they may even have fainting episodes. For years, the gold standard treatment for rheumatic aortic stenosis was valve replacement with open-heart surgery.
However, thanks to incredible advances in medicine, it is now also possible to replace the aortic valve by entering through the groin. This method, called TAVI (Transcatheter Aortic Valve Implantation), has become a lifeline especially for elderly patients, those with other serious health problems, and those considered too risky to undergo surgery. In the TAVI procedure, a new biological valve, folded at the tip of a catheter as thick as a pen, is placed. Once the heart is reached through the groin, this new valve is positioned inside the narrowed old valve, inflated, and opened. The new valve pushes the old valve toward the walls and immediately begins to perform its function. Patients can stand up in a very short time after this miraculous procedure.
Can the Clipping Method Be Applied in Valve Insufficiency Caused by Rheumatic Heart Disease?
If rheumatic heart disease not only causes narrowing in the valves but also damages the valve structure and leads to blood leaking backward, that is, serious insufficiency, the situation is managed somewhat differently. Because the valve cannot close completely, with each heartbeat some of the blood flows backward toward the lungs and may leave the patient so breathless that they feel as if they are suffocating. Non-surgical methods have also been developed for this leakage problem.
The best known of these is the clipping method called MitraClip. By reaching the heart through the groin vessel, the two valve leaflets that cannot close completely and have moved away from each other are attached to each other from the middle with a special metal clip. This small clip helps the valve close better as a whole and significantly reduces leakage. However, there is a very important detail here; because rheumatic valves are structurally thickened and prone to sticking, very careful measurements must be made when applying the clipping procedure. Because while trying to prevent leakage, there is a risk of narrowing the valve opening too much and this time causing artificial mitral stenosis. This fine adjustment is shaped by the experience of the specialist performing the procedure.
Does Rheumatic Heart Disease Create a Risk During Pregnancy?
The female body experiences a miracle during pregnancy, but this miracle is a major stress test on the heart. As the baby grows, the mother’s blood volume increases by about one and a half times, and the heart rate rises. If the expectant mother has a rheumatic stenosis in her heart that has not caused many symptoms until that day, then things become complicated. This increased amount of blood cannot pass comfortably through the narrowed heart valve.
As a result, blood begins to pool in the lungs. An expectant mother who would normally climb stairs comfortably may become unable to breathe even while sitting, and fluid may accumulate in her lungs. In this dangerous situation, interventional methods come into play in addition to medication treatment so as not to endanger the life of both the mother and the baby. Especially in the second trimester of pregnancy, when the baby’s organ development is complete but the mother’s blood load has greatly increased, a balloon (PMBV) procedure can be performed on the mother using special radiation protectors. This procedure is extremely safe during pregnancy; with the widening of the valve, the mother is immediately relieved and can complete her pregnancy healthily and hold her baby in her arms.
What Should Be Done to Prevent Rheumatic Heart Disease Attacks?
The success of the disease treatment depends not only on the perfection of the procedure performed but also on the patient’s life after the procedure. The body’s immune system has a memory; if a beta-hemolytic streptococcus germ settles in your throat again, the immune system remembers this and may restart its destructive attack on the heart. This is called a flare-up of the disease. Even if the heart valve has been treated, a new attack can damage that valve again.
To protect against these insidious attacks, patients must follow certain basic rules throughout their lives.
The main steps to pay attention to are as follows:
- Regular penicillin protection
- Attention to oral hygiene
- Precautions before dental treatments
- Rapid intervention in throat infections
- Routine cardiology checkups
The backbone of this protection is preventing streptococcal infections, which trigger the disease. Since bacteria accumulating in the gums can also reach the heart through the bloodstream and settle on damaged valves, patients with rheumatic heart disease must pay extra attention to their toothbrushing habits and must take protective antibiotics before any dental intervention involving bleeding.
Which Medication Groups Should Patients with Rheumatic Heart Disease Use?
Whether or not valve intervention is performed with interventional methods, patients diagnosed with rheumatic heart disease need certain medical supports that they must use regularly in their daily lives. These medications aim to reduce the workload of the heart, prevent new attacks, and protect the patient from life-threatening risks.
The medication groups that patients need to use regularly are as follows:
- Long-acting penicillin injections
- Blood thinner tablets
- Heart rate regulators
- Diuretics
- Blood pressure stabilizers
The penicillin injections on this list, usually administered every 21 or 28 days, act as a shield against a new germ attack and must never be skipped until the age determined by the doctor. Another vital medication group is blood thinners. Damage in the heart valves can cause rhythm disorders in the heart’s atria (atrial fibrillation). When the rhythm is disturbed, blood begins to clot inside the heart. If these clots break off and travel to the brain, they can cause a stroke. To eliminate this stroke risk, using strong blood thinners whose dose is adjusted under medical supervision is an indisputable necessity for the patient’s health. Diuretics relieve shortness of breath by removing excess fluid accumulated in the lungs or legs from the body. Patients should not change the dose of their medications or stop them without consulting their doctors; this is the golden rule of a long and healthy life.

Prof. Dr. Kadriye Orta Kılıçkesmez is one of the leading figures in the field of Turkish cardiology. She was born on January 24, 1974, in Tekirdağ. After completing her undergraduate education at Istanbul University Cerrahpaşa Faculty of Medicine, she chose cardiology as her specialty and received her specialist training at the Cardiology Institute of the same university. In 2015, she was appointed by the university to establish the Şişli Etfal cardiology clinic and Angio laboratory. Becoming a professor in 2017, Kadriye Kılıçkesmez established the cardiology clinic and Angio laboratory of Prof. Dr. Cemil Taşçı Hospital in 2020 and ensured that the clinic became a training clinic.