Türkçe
 Français
 Deutsch
 Italiano
 Español
 العربية
 Русский

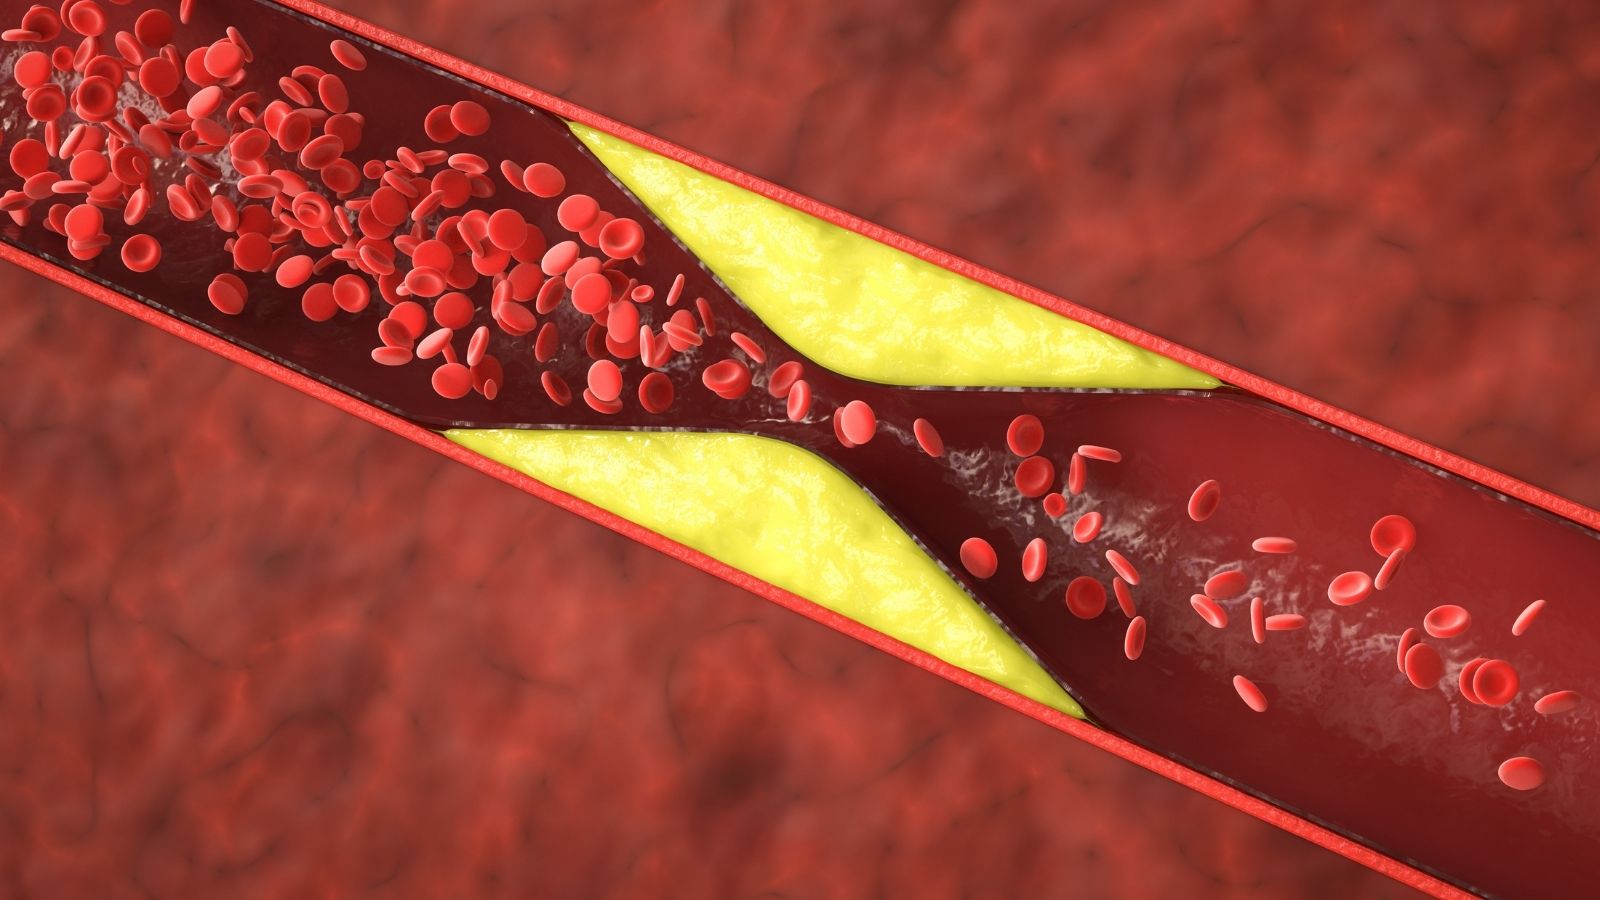
Mitral valve thickening is a condition in which the two-leaflet valve system that allows blood to pass between the left atrium and the left ventricle of the heart gradually loses its thin, flexible structure and becomes stiff. This tissue, which normally opens and closes smoothly like a very thin sail, loses its natural ability to move as a result of changes in its cellular structure, becoming calcified or extremely rigid.
The severity of this condition depends on how much the thickening restricts the mechanical function of the valve. A mild structural change does not pose an immediate life-threatening risk. However, when the valve completely loses its flexibility and can no longer allow blood to flow forward or permits blood to leak backward, this marks the beginning of a dangerous process that directly strains the heart and creates conditions for heart failure.
This anatomical deterioration, which dramatically increases the heart’s workload over time, leads to increased pressure in the pulmonary blood vessels and circulatory imbalances. Bringing the mechanical burden imposed on the heart by this physical change in the valve under control in a timely manner is a vital step in preventing permanent damage.
What Causes Mitral Valve Thickening and Which Diseases Contribute to Its Development?
The processes that cause thickening and restricted movement of the mitral valve leaflets generally arise from several different causes. Correctly identifying these causes is an important step in determining the treatment strategy to be applied. One of the first and most common causes is a history of rheumatic heart disease. Particularly when bacterial throat infections, commonly known as beta streptococcal infections, occurring during childhood or early adolescence are not adequately treated, a reaction called acute rheumatic fever may develop in the body. While the immune system fights the bacteria, it may also affect the inner lining of the heart and valve tissues because of structural similarities. This initiates a chronic inflammatory process in the valves that may continue for many years. Over decades, the edges of the valve leaflets begin to thicken, the areas where the leaflets meet may stick together, and the thread-like structures supporting the valve may shorten and become stiff.
The second common factor is degenerative processes and calcification associated with advancing age. With aging, the valve fibers, which open and close approximately one hundred thousand times a day, are subjected to mechanical fatigue. Over time, certain changes occur in the cellular structure of the valve, and calcium begins to accumulate between the tissues. When calcium, which is normally expected to be found in bones, spreads from the base of the valve throughout the tissue, a hardened structure may develop. Conditions such as high blood pressure, declining kidney function, and diabetes can accelerate this calcium accumulation process.
A third factor is a condition known as myxomatous degeneration, in which the supporting framework of the valve becomes structurally weakened. In this condition, the quality of the valve’s supporting tissues changes, and the leaflets may become excessively thickened, larger than normal, redundant, and loose. When the heart contracts, these loose leaflets may bend toward the left atrium, causing a displacement known as prolapse.
What Complaints and Symptoms Does Mitral Valve Thickening Cause in the Body?
Mitral valve thickening generally progresses silently in its early stages and may not cause any noticeable discomfort. However, when the thickening progresses and impairs the mechanical function of the valve, meaning that the valve can no longer open or close adequately, the dynamics of blood flow within the heart change. The abnormal pressure wave generated inside the heart chambers is transmitted backward toward the pulmonary blood vessels from which the blood arrives. When pressure increases in the tiny capillaries of the lungs, fluid inside the blood vessels begins to leak into the air sacs of the lungs. This condition forms the main source of the discomfort experienced by the patient. Initially, a person may only notice becoming tired more quickly than before when climbing stairs, walking uphill, or performing physically demanding tasks.
The main symptoms that patients may experience as mitral valve thickening progresses include:
- Shortness of breath
- Palpitations
- A feeling of suffocation at night
- Fatigue with minimal exertion
- Swelling in the legs
- Edema in the ankles
- Abdominal bloating
- Bloody sputum
As the disease progresses, these symptoms may also occur at rest. Lying flat at night may become difficult, and the patient may wake up feeling suffocated and need to place additional pillows under their head. A further increase in pulmonary pressure also begins to strain the right heart muscle. When the right heart muscle cannot adapt to this burden, fluid begins to accumulate in the lower parts of the circulatory system. Prominent neck veins and edema in the lower parts of the body may develop. In other words, if left untreated, this change in the valve may develop into a more extensive problem affecting the lungs and the body’s overall circulation.
Is Mitral Valve Thickening Dangerous and When Does It Progress?
The statement “mild mitral valve thickening” in a medical examination report may not indicate an immediate life-threatening condition as long as valve function and blood flow remain normal. However, when thickening progresses and disrupts the mechanical balance of the valve, a more cautious approach is required. Under normal conditions, the area of a fully opened mitral valve is wide and allows blood to pass easily. When this area narrows as a result of thickening, tissue adhesions, and calcification, the lower chamber of the heart begins to receive insufficient blood. When the area decreases below a certain threshold, a condition known as “mitral stenosis” develops. Similarly, when thickened leaflets that have lost their flexibility cannot close completely, some of the fresh blood that the heart should pump leaks backward toward the vessels coming from the lungs.
Another important problem that a thickened and damaged valve may cause is heart rhythm irregularities and the associated risk of blood clot formation. When the upper chamber of the heart is continuously exposed to high pressure, it may enlarge over time. This chronic stretching can affect the electrical conduction of heart muscle cells, creating conditions for a rhythm disorder known as atrial fibrillation. When this rhythm disorder develops, the upper chamber of the heart stops contracting rhythmically, and blood flow slows down. Stagnant blood may gradually develop a tendency to clot. Fragments of these clots may break away and travel to the blood vessels of the brain, potentially causing neurological conditions known as stroke. Therefore, significant structural deterioration of the valve may initiate a chain reaction that can affect not only the heart but also other organs.
Which Tests Are Used to Diagnose Mitral Valve Thickening?
Echocardiography is the primary examination method we use to determine the degree of structural change in the valve, its effect on the heart, and the appropriate treatment alternative. With standard cardiac ultrasound performed through the chest wall, sound waves can be used to measure the thickness of the valve leaflets and examine where calcification has accumulated. In addition, Doppler technology makes it possible to calculate the speed and direction of blood passing through the valve and the actual open area of the valve. This examination is generally a very comfortable and painless process for patients.
More detailed mapping may be necessary before planning a repair using interventional methods. For this purpose, transesophageal echocardiography (TEE) may be performed by inserting a thin probe through the mouth into the esophagus to obtain images of the heart from behind. This examination allows the valve structure and the surfaces where the leaflets come into contact with each other to be evaluated much more clearly and in three dimensions. It also provides a better opportunity to examine whether any blood clots have formed inside the heart chambers.
In patients with valve stenosis, certain specialized scoring systems are used to evaluate whether the valve is suitable for nonsurgical balloon treatment. This assessment scores the mobility of the valve, the degree of leaflet thickening, the level of calcification, and the condition of the thread-like supporting structures beneath the valve. Based on the results of this examination, a decision is made as to whether the valve structure is ideal for nonsurgical methods or whether a different strategy would be safer.
Can Medication Be Sufficient for Mitral Valve Thickening?
When valve thickening or associated loss of function is diagnosed in our patients, the first question that comes to mind is whether this condition can be resolved with medication. However, drug treatments cannot physically eliminate the anatomical and mechanical causes of the disease. The main purpose of medications is to relieve the patient’s symptoms and balance the workload placed on the heart.
For example, diuretic medications can help remove excess fluid accumulated in the body and lungs, thereby relieving the sensation of shortness of breath. Medications that regulate heart rhythm or slow the heart rate can support circulation by giving the heart a little more time for blood to pass through the narrowed valve. Blood pressure medications can reduce the resistance the heart encounters while pumping blood. However, medications cannot dissolve valve leaflets that have thickened, hardened, or become calcified over the years, nor can they restore the tissues to their former flexible structure. The mechanical obstruction or closure defect in the valve continues to exist as a physiological condition. Therefore, although medication is a necessary step in improving the patient’s quality of life, a permanent solution in advanced valve disorders can generally be achieved through mechanical repair or replacement of the valve.
How Is the Nonsurgical Balloon Method Performed in the Treatment of Mitral Valve Thickening?
In cases of stenosis that develop due to a history of rheumatic disease, where the leaflet edges have fused together but have not become excessively calcified, percutaneous balloon mitral valvuloplasty is a highly effective treatment option. This procedure is based on the principle of widening the narrowed valve without opening the chest while preserving the patient’s own natural valve.
The procedure is generally performed in specialized angiography laboratories after administering mild sedation and local anesthesia to the patient. Very thin guidewires are introduced through the vein in the groin to reach the right atrium of the heart. A small opening is created in the thin septum separating the right and left chambers of the heart to enter the left atrium. From there, a specially designed balloon catheter, with the balloon at its tip in a deflated state, is positioned precisely in the center of the narrowed mitral valve.
Under X-ray imaging and ultrasound guidance, this balloon is inflated at the level of the valve. As the balloon expands, it separates the fused leaflet edges outward, widening the valve opening within seconds. Once the obstruction is relieved, the excessive pressure in the left atrium generally begins to decrease rapidly. Because the patient’s own valve tissue is preserved, the need for lifelong blood-thinning medication, as required with mechanical prosthetic valves, may be avoided. Patients can usually stand up and return to their daily lives within a relatively short period after the procedure.
What Is the Clipping Procedure for Mitral Valve Thickening and Regurgitation?
If the patient’s main problem is not valve stenosis but the inability of the valve to close completely as a result of thickening, structural relaxation, or weakening of the supporting cords, the clipping method (MitraClip) may be considered to prevent backward blood leakage. This procedure represents an important treatment alternative, particularly for elderly patients or those at high risk for open-heart surgery.
In this method, the heart is again accessed through the vein in the groin, and a very small, steerable clip system is located at the tip of the catheter. Guided by live images obtained through three-dimensional echocardiography, this clip is brought close to the areas of the valve that cannot close completely and allow blood to leak backward. The leaflets with the closure defect are grasped and fastened together using this clip. Thus, a single enlarged valve opening is transformed into a double-opening system joined at the center, improving the valve’s ability to close.
During the procedure, the amount of blood leaking backward is monitored in real time using ultrasound. When necessary, more than one clip may be placed to reduce the leakage as much as possible. This procedure can contribute significantly to reducing symptoms and the need for hospitalization in patients who continue to experience fatigue and shortness of breath despite medication.
Can Valve Replacement Through the Groin Be Performed in Cases of Severely Calcified Mitral Valve Thickening?
In some patient groups, the mitral valve leaflets not only become thickened but also develop extensive calcium deposits that surround the entire valve framework. Surgically removing calcium from and replacing this valve, which has become as hard as stone, may be considered high risk in some patients because of the potential to damage the structure of the heart. Similarly, a biological valve previously implanted through open surgery may have degenerated over time and lost its function.
In such more challenging anatomical situations, transcatheter valve replacement methods may be considered. In this procedure, a new biological valve that has been specially compressed and reduced in size is attached to the tip of a catheter system. Using this system advanced through the groin, the new valve is positioned directly inside the patient’s severely calcified valve or old, deteriorated prosthesis. This new valve, which is expanded with a balloon or opens on its own, anchors firmly inside the old tissue. Thus, the valve mechanism is renewed without opening the chest or removing the old valve tissue from its position. These procedures, which require advanced technology, are performed following meticulous imaging and careful planning tailored to the individual patient.
What Are the Advantages of Interventional Methods in the Treatment of Mitral Valve Thickening?
Open-heart surgery remains a highly reliable and necessary method in the treatment of many heart valve diseases today. However, with the current advances in medicine, procedures performed through blood vessels without opening the chest offer significant innovations in patient comfort for suitable individuals.
The general advantages that nonsurgical interventional procedures provide to patients include:
- No cutting of the breastbone
- Shorter duration of deep general anesthesia or the possibility of using local anesthesia
- No need for connection to a heart-lung machine
- No formation of large surgical scars
- A significant reduction in the need for blood transfusions
- A much shorter stay in intensive care
- The possibility of a rapid return to normal daily life and physical activities
These methods can help reduce the fatigue and risks associated with treatment, particularly for elderly patients or individuals with additional health problems affecting organs such as the lungs or kidneys. Because patients are generally treated through a small access point in the groin area, the recovery period is quite short.
What Should People Diagnosed With Mitral Valve Thickening Pay Attention to in Daily Life?
Individuals whose echocardiography examinations reveal valve thickening are advised to keep their condition under regular observation and adopt lifestyle habits that support heart health. To prevent mild thickening that does not yet require intervention from placing additional strain on the heart, attention should be paid to general vascular health and blood pressure control.
Some of the precautions these patients are advised to take in their daily lives include:
- Reducing daily salt consumption
- Taking regular, light-paced walks as recommended by the physician
- Maintaining an ideal body weight
- Strictly avoiding smoking and tobacco products
- Not neglecting regular echocardiography examinations
- Paying attention to oral hygiene to prevent tooth and gum infections
- Consulting a physician without delay when experiencing palpitations or shortness of breath

Prof. Dr. Kadriye Orta Kılıçkesmez is one of the leading figures in the field of Turkish cardiology. She was born on January 24, 1974, in Tekirdağ. After completing her undergraduate education at Istanbul University Cerrahpaşa Faculty of Medicine, she chose cardiology as her specialty and received her specialist training at the Cardiology Institute of the same university. In 2015, she was appointed by the university to establish the Şişli Etfal cardiology clinic and Angio laboratory. Becoming a professor in 2017, Kadriye Kılıçkesmez established the cardiology clinic and Angio laboratory of Prof. Dr. Cemil Taşçı Hospital in 2020 and ensured that the clinic became a training clinic.